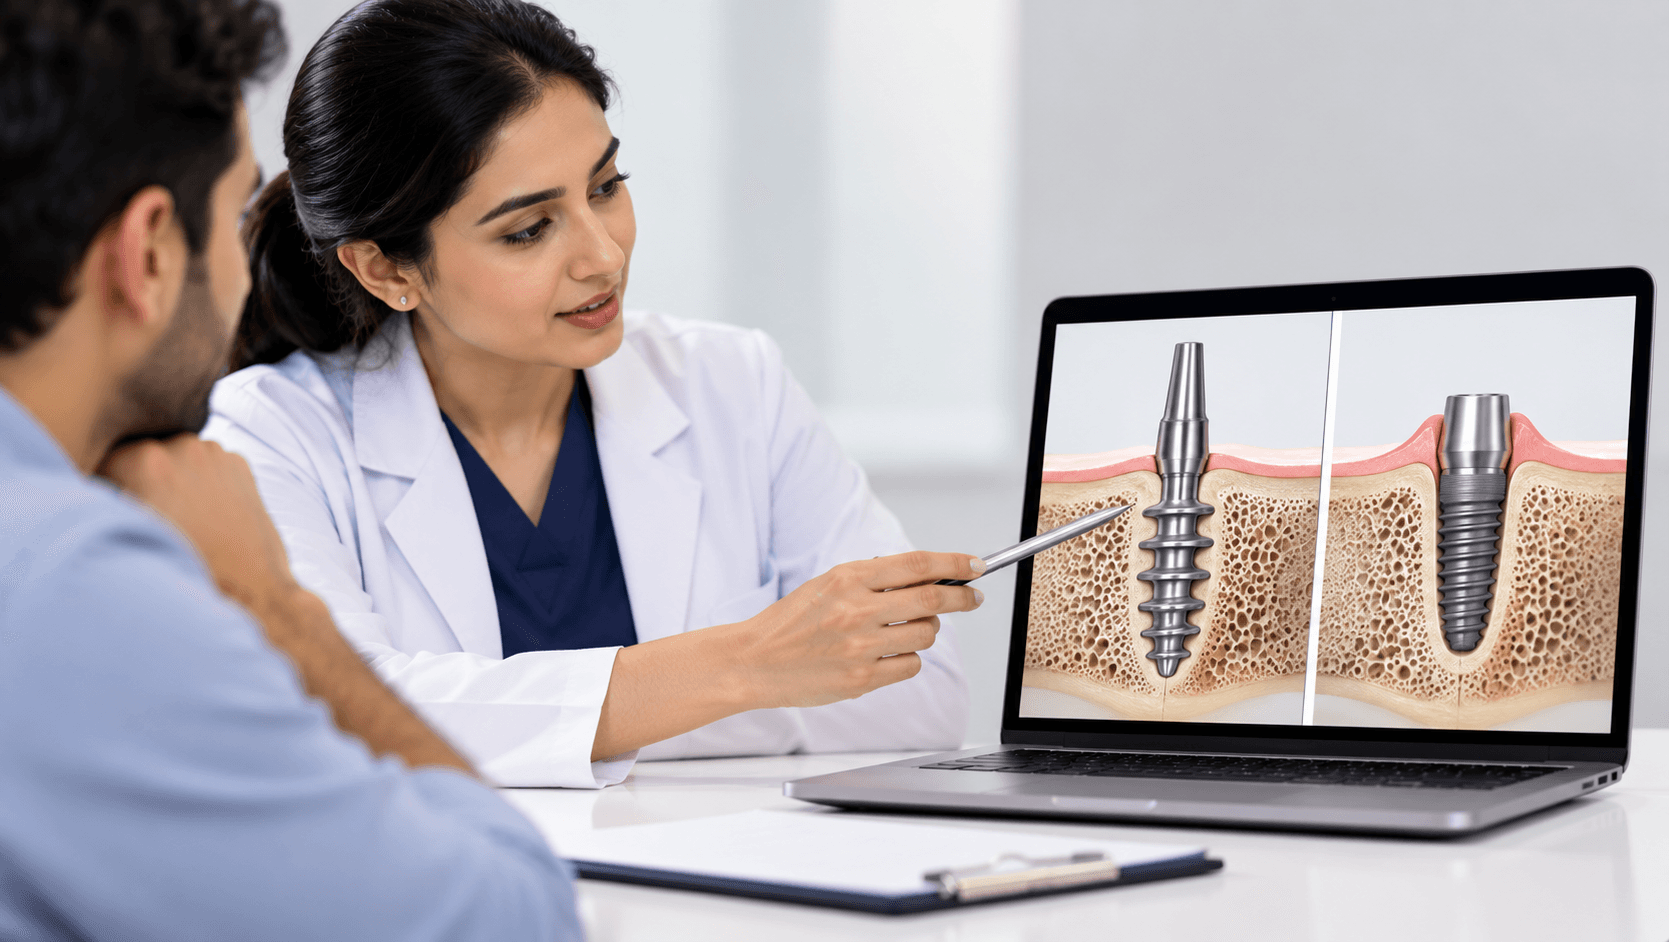
Basal Implants vs Conventional Dental Implants: A Dentist's Guide
Basal implants vs conventional dental implants is a comparison many general dentists in India are asked about by patients, especially those with severely resorbed jaws who have been told they need bone grafting. Basal implants are often marketed as a quick, graft-free solution with teeth fixed within days, while conventional root-form implants remain the most widely researched option in implant dentistry.
Both approaches have a place, but they rely on different biological and mechanical principles. This article explains how they differ, when each may be indicated, what immediate loading really involves, and the limitations every dentist should understand before offering or referring for either treatment.
What Are Basal Implants?
Basal implants, sometimes called cortical, bicortical or strategic implants, are designed to engage the dense cortical bone of the jaws rather than relying mainly on the crestal and cancellous bone around a conventional implant. The term basal refers to the basal bone, which is more resistant to resorption than the alveolar process.
Designs vary. Some are inserted laterally into a slot prepared in the bone and carry one or more horizontal discs; others are screw-type implants with a thin, polished shaft and aggressive threads placed through a flapless or minimally invasive approach to reach cortical bone, sometimes in regions such as the pterygoid plates or the nasal floor. Most are single-piece, with the abutment and implant body as one unit.
How Do Conventional Dental Implants Differ?
Conventional dental implants are typically two-piece, root-form titanium or titanium-alloy fixtures placed into the alveolar bone. They depend on osseointegration, the direct structural and functional connection between living bone and the implant surface described in Branemark's work, and their surfaces are usually roughened to support bone apposition.
Loading protocols range from delayed loading, allowing a healing period before restoration, to early and immediate loading when primary stability and case conditions allow. When bone volume is inadequate, conventional protocols often use guided bone regeneration, sinus augmentation, short or narrow implants, or tilted implant concepts to achieve an acceptable result.
The two-piece design allows the clinician to select abutments, correct angulation, change prostheses and retrieve components, which gives considerable prosthetic flexibility and a long track record in the literature.
When Are Basal Implants Indicated?
Proponents usually suggest basal implants for patients in whom conventional implants would require extensive grafting. Commonly described situations include:
1. Severely atrophic ridges
Patients with advanced resorption, particularly in the posterior maxilla or mandible, where anchorage in residual cortical bone may avoid sinus lifts or block grafts.
2. Patients who cannot undergo grafting
Some medically or financially constrained patients may prefer to avoid multiple surgeries and long treatment times.
3. Full-arch immediate rehabilitation
Basal implants are frequently used to support cross-arch splinted fixed prostheses placed shortly after surgery.
Even in these cases, conventional alternatives such as short implants, tilted implants, zygomatic implants or grafting procedures should be considered and discussed with the patient.
How Should Dentists Approach Case Selection?
Good case selection is the single most important factor in implant success, whichever system is used. Start with a thorough medical history, noting uncontrolled diabetes, smoking, bisphosphonate or antiresorptive therapy, radiotherapy to the jaws and bleeding disorders, all of which influence healing and risk.
Evaluate the available bone in three dimensions with CBCT, identifying the inferior alveolar canal, mental foramen, maxillary sinus, nasal floor and cortical plates. Assess bone density, inter-arch space, smile line, lip support and the opposing dentition. Parafunction such as bruxism increases mechanical load and needs to be factored into the prosthetic design.
Prosthetically driven planning should come first: decide where the teeth need to be, then choose implant positions and the implant type that can support that result predictably. Where conventional implants can achieve the plan with acceptable morbidity, they are often the more flexible and better-documented choice. Where bone loss is extreme and the patient understands the trade-offs, a basal implant approach may be discussed as one of several options.
Finally, consider maintenance. Patients must be able to clean around the prosthesis and attend regular reviews, since peri-implant mucositis and peri-implantitis can affect any implant system.
What Does Immediate Loading Mean with Basal Implants?
Immediate loading means placing a functional prosthesis within a short period after implant placement rather than waiting for osseointegration to complete. With basal implant protocols, a fixed, cross-arch splinted prosthesis is commonly delivered within a few days of surgery. Splinting distributes occlusal forces across multiple implants and limits micromovement, which is critical during early healing.
The success of immediate loading depends on achieving adequate primary stability, careful occlusal design with balanced contacts and controlled cantilevers, and patient compliance with diet and hygiene instructions. Immediate loading is not unique to basal implants; conventional implants are also loaded immediately in carefully selected cases.
What Are the Limitations of Basal Implants?
Dentists should be aware of several limitations. The long-term evidence base for basal implants is smaller than for conventional root-form implants, and much of it comes from case series rather than controlled trials. They are not endorsed as a routine first-line option by all implant organisations.
Single-piece designs offer limited abutment options. Angulation is often corrected by bending the neck, which requires skill and restricts later adjustments. Surgical access to pterygoid or other distant anatomical sites carries risks to vital structures, so detailed CBCT-based planning and advanced surgical training are essential.
Because the prosthesis is usually splinted, failure of one implant can affect the whole restoration. Maintenance, hygiene access and the management of complications also need to be planned from the outset. Informed consent should present all realistic options, including conventional and grafting approaches.
Frequently Asked Questions
Are basal implants better than conventional implants?
Neither is universally better. Conventional implants have the broadest long-term evidence, while basal implants may be an option for selected atrophic cases. Case selection and operator training matter more than the implant type alone.
Can a general dentist place basal implants?
Basal implantology requires specific surgical training, strong knowledge of anatomy and careful planning with CBCT. General dentists should gain structured, supervised training before placing them.
Do basal implants avoid bone grafting?
They are designed to use existing cortical bone and can reduce the need for grafting in some cases. They do not make grafting obsolete, and conventional augmentation remains appropriate in many situations.
Is CBCT necessary for basal implant planning?
Three-dimensional imaging is strongly recommended for planning any implant in compromised bone, and it is particularly important when engaging distant cortical structures close to the sinus, nerve canals or pterygoid region.
Conclusion
Understanding basal implants vs conventional dental implants helps you give patients balanced advice. Conventional implants remain the evidence-based standard for most situations, while basal implants may offer a graft-free option for carefully selected atrophic cases when placed by adequately trained clinicians.
If you want to build confidence in implant case selection, surgical planning and prosthetic design, MCDI's hands-on implantology courses, including basic to advanced implant training, cover conventional protocols and introduce newer concepts in a structured clinical setting. Speak to the MCDI team to find the course that matches your experience.